Confirm resectability
Confirm whether a complex perihilar tumor can be resected.

At Quenet-Torrent Institute we treat cholangiocarcinomas with high-complexity hepatobiliary surgery and a multidisciplinary team.
CONTACT SPECIALISTBile duct cancer (cholangiocarcinoma) requires high-complexity hepatobiliary surgery: major hepatectomy with bile duct resection and reconstruction. At Quenet-Torrent Institute (Barcelona · Madrid), Prof. Fabrizio Panaro, together with Dr. Quenet and Dr. Torrent, performs this approach in both hilar (Klatskin) and distal cholangiocarcinomas.
Bile duct cancer, or cholangiocarcinoma, is a malignant tumor that arises in the lining of the bile ducts. By location it can be classified as intrahepatic, perihilar (Klatskin tumor) or distal.
Risk factors include primary sclerosing cholangitis, choledochal cysts, liver fluke infection, hepatolithiasis and inflammatory bowel disease. The main symptoms are jaundice, itching, weight loss and abdominal pain.
Surgery is the only potentially curative treatment. However, the anatomical complexity of the bile ducts means these operations require a specialized team.
Obstruction of the bile duct is the central mechanism behind the symptoms of cholangiocarcinoma. The most characteristic sign is jaundice, that is, yellowing of the skin and the whites of the eyes, which appears when bile cannot drain properly into the intestine. It is usually accompanied by intense itching, dark urine and pale or clay-colored stools.
As the disease progresses, weight and appetite loss, fatigue and abdominal pain in the right upper quadrant, where the liver and gallbladder are located, are common. Some patients may have fever if there is cholangitis, that is, an infection of the bile duct caused by the obstruction. With any of these symptoms, especially recent-onset jaundice, it is necessary to see a specialist without delay to begin the diagnostic workup.
Cholangiocarcinoma does not usually have a single identifiable cause, but it has been linked to several conditions that cause chronic inflammation or ongoing damage to the lining of the bile ducts. Among the best established factors is primary sclerosing cholangitis, a chronic inflammatory disease of the bile ducts that considerably increases the risk of malignant change. Choledochal cysts, intrahepatic gallstones and chronic bile duct infections, including some liver fluke infections, are also associated.
Other conditions that increase the risk are inflammatory bowel disease, particularly ulcerative colitis, as well as chronic liver disease and cirrhosis of any cause. Older age also plays a part, since most cases are diagnosed from the age of sixty. In many patients no specific risk factor is identified, which makes clinical evaluation especially important when there are suggestive symptoms.
In a complex case, a second opinion can open up options for surgery with curative intent.
Confirm whether a complex perihilar tumor can be resected.
Assess which type of hepatectomy is needed and whether the remaining liver will be sufficient.
Optimize preoperative biliary drainage to improve liver function.
Consider neoadjuvant chemotherapy or liver transplantation in selected cases.
Many patients considered inoperable can benefit from an assessment at a specialized center.
Surgical treatment varies according to the location of the tumor.
For perihilar (Klatskin) tumors, with biliodigestive reconstruction.
For intrahepatic cholangiocarcinomas, resection of the affected liver tissue.
For tumors of the distal common bile duct, Whipple surgery.
For tumors of the middle bile duct, with reconstruction.
The strategy is tailored to location, extent and the patient's condition.
These are the tests and techniques we use to prepare and plan these operations.
Detailed mapping of the biliary anatomy and tumor extent.
Evaluation of the relationship with vascular structures.
Calculation of the functional liver remnant after resection.
Optimization of liver function before surgery.
Growth of the future liver remnant when necessary.
Quenet-Torrent Institute treats cholangiocarcinoma with teams specialized in hepatobiliary surgery.
We focus on advanced cancer and complex tumors, with techniques such as major hepatectomy with bile duct resection, which not every center offers.
Surgeons, oncologists, radiologists, nutritionists and psychologists review your case together.
We follow the published scientific evidence and review our protocols when new data appear.
We have MR cholangiography, multislice CT, 3D liver volumetry, biliary drainage and portal vein embolization to prepare and plan each resection.
We explain each step of the treatment and answer your questions throughout the process.
Surgeons on the team who treat bile duct cancer.

Oncological surgeon
View doctor: Dr. François Quenet"Surgeon with expertise in gastrointestinal and hepatobiliary tumors and in highly difficult operations."

Oncological surgeon
View doctor: Dr. Juan José Torrent"Specialist in gynecological tumors, peritoneal carcinomatosis and complex oncological surgery."
Answers to the most common questions about diagnosis, treatment and prognosis.
Yes, when a complete resection with a clear margin is achieved. Surgery is the only potentially curative treatment for cholangiocarcinoma, and it is combined with chemotherapy. The difficulty lies in its location: it grows next to the main vessels and bile ducts, which limits operability.
It is perihilar cholangiocarcinoma, located where the right and left hepatic ducts join, just as they leave the liver. It is the most common bile duct tumor and the most complex to operate on, because of how close it is to the main vessels.
Because the tumor spreads along the bile ducts into the liver. To obtain a clear margin, the corresponding liver lobe has to be removed together with the affected bile duct, and bile drainage then has to be reconstructed. Without that resection, the margin is compromised.
It is the placement of a drain or a stent to unblock the bile duct before surgery. It relieves jaundice and allows the liver to recover its function, so that it is in better condition for major surgery. It is not always necessary: it is indicated according to the bilirubin level and the planned extent of surgery.
The hospital stay is usually 10 to 14 days and full recovery takes between 2 and 3 months. It is a demanding operation because it combines liver resection and biliary reconstruction. Discharge is decided by how liver function and the drain evolve, not by a fixed timeline.
In many cases, yes. Chemotherapy after surgery improves long-term results, especially when lymph nodes are involved or the margin was narrow. In unresectable tumors, chemotherapy and targeted treatments based on the molecular profile are the basis of the approach.
In very selected cases of unresectable perihilar cholangiocarcinoma, a liver transplant can be considered, within strict protocols that include prior chemoradiotherapy. The selection criteria are demanding and the assessment must be made at a center with a transplant program and experience in this indication.
At centers with proven experience in complex hepatobiliary surgery, because treatment combines liver resection, biliary reconstruction and sometimes vascular reconstruction. It is worth asking how many cases of this kind the team treats each year and whether it has interventional radiology and a multidisciplinary board.
We operate in two private hospitals in Spain. The same medical team treats you in Madrid and in Barcelona, with the same surgical and oncological protocols.

Private hospital in Pozuelo de Alarcón with a multidisciplinary team specialised in digestive surgical oncology.
View Memorial Publio Cordón Hospital
Private hospital in Barcelona where the team performs high-complexity surgical oncology.
View Centro Médico TeknonReal testimonies from patients treated by our team in high-complexity surgical oncology.
66-year-old English woman with advanced ovarian cancer and peritoneal metastases. Treated with cytoreduction + HIPEC, she is now disease-free.
Read the full case73-year-old patient with advanced cancer treated with chemotherapy and high-complexity surgical oncology, with good survival and quality of life.
Read the full caseA mistaken diagnosis of terminal colon cancer that a second opinion revealed to be pseudomyxoma peritonei, treatable with cytoreductive surgery and HIPEC.
Read the full caseDiagnosed with widespread peritoneal carcinomatosis and considered inoperable. After complete cytoreduction with HIPEC, today his is a story of survival.
Read the full caseWonderful surgical team, among the best out there. Dr. Torrent (expert in peritoneal carcinomatosis) is an exceptional surgeon and an even better person. His coordinator is super kind, fast and efficient. The personal care is excellent and so are the results. This is of vital importance for cancer patients.
In the public healthcare system they gave my father a maximum of one year to live. They only offered him chemo and no hope, said it was impossible, that nothing could be done. He had several tumors inside the peritoneal sac with metastases. A year and a half later he is clean, completely cured. His latest PET scan came back clean. We are very happy. Thanks to Dr. Torrent and his team. THANK YOU.
Excellent professionals, especially Dr. Torrent, attentive at all times to the patient (my wife), operated for peritoneal pseudomyxoma. They helped us with all our needs since we came from outside Barcelona. Thank you Elisabeth. We are very grateful to Quenet Torrent Institute, thank you for everything.
I am a 63-year-old patient. They detected adrenal gland cancer and told me there was nothing to be done. I sought a second opinion and they told me about the Quenet Torrent team, specialists in complex operations. Dr. Torrent, from the first moment, told me they could operate. They operated and removed a large tumor mass. I spent a week in the ICU and a month on the ward. Every day he came morning and evening, no matter Saturday or Sunday. Never throw in the towel. I am happy to have found these professionals who gave me my life back. Thank you.
Many thanks for your attention. Dr. Torrent always attentive, involved and decisive. The reception staff very pleasant and always offering the best option. 100% RECOMMENDED. THANK YOU.
Dr. Torrent helped me make the best decision at a difficult moment. I think he is a great professional and a person capable of accompanying you and putting himself in another's shoes. Thank you for everything.
I have peritoneal carcinomatosis. When I sent my diagnosis to every center, practically all of them agreed on palliative chemo with little survival time, since I had a very aggressive type of cell. Until we reached Dr. Quenet, Dr. Torrent and their team. I can only confirm what their CV announces: they are far ahead of the rest. They saved my life, because during the operation the harmful cells that everyone had diagnosed, and that were the reason nobody would operate on me, were not there. This intervention has become the best investment of my life.
The best decision of my life was finding this excellent team of surgeons who saved my husband's life. At a prestigious international clinic in Madrid he was given up for lost with advanced peritoneal carcinomatosis from appendiceal cancer, and thanks to them, the best professionals in this field, he was operated on very successfully. A perfect recovery with no complications, because they were on top of his progress at all times. They have a great quality: from the start they were very honest and close. I can only be deeply grateful; we went to buy time and thanks to them my husband got his life back.
Dr. Torrent is a brilliant surgeon and a very approachable and warm doctor, whose manner reveals all the qualities that make him a great person and professional: perseverance, innate curiosity and a desire to learn, humility, sincerity and empathy. Going through an operation is undoubtedly an intense experience, physically and emotionally, in which anxieties arise and you feel very vulnerable. All of that is normal, and as his former patient I can say that his care and professionalism throughout the process were absolutely exceptional. I felt very supported by him, with the confidence of knowing I was in the best hands. I will always be grateful to him. Moltes gràcies Dr. Torrent!
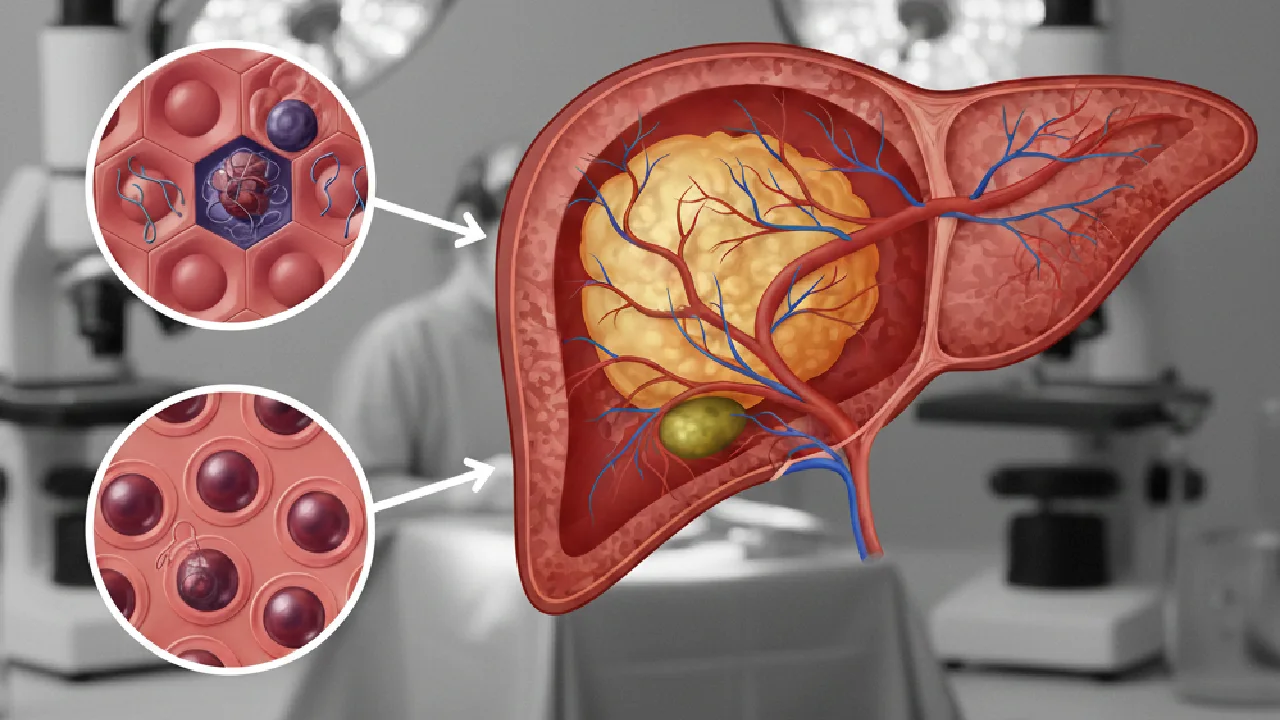
Resection is the only potentially curative treatment for liver metastases. What makes a case operable, and what to do if you have been told it is not.
The success of oncological surgery depends on many factors: the surgeon's experience, complete cytoreduction, a multidisciplinary team and perioperative care.
The centre and the surgical team influence the outcome of cancer treatment. What criteria to look at before deciding.
Complete the form and schedule your appointment to speak directly with the surgeon.