
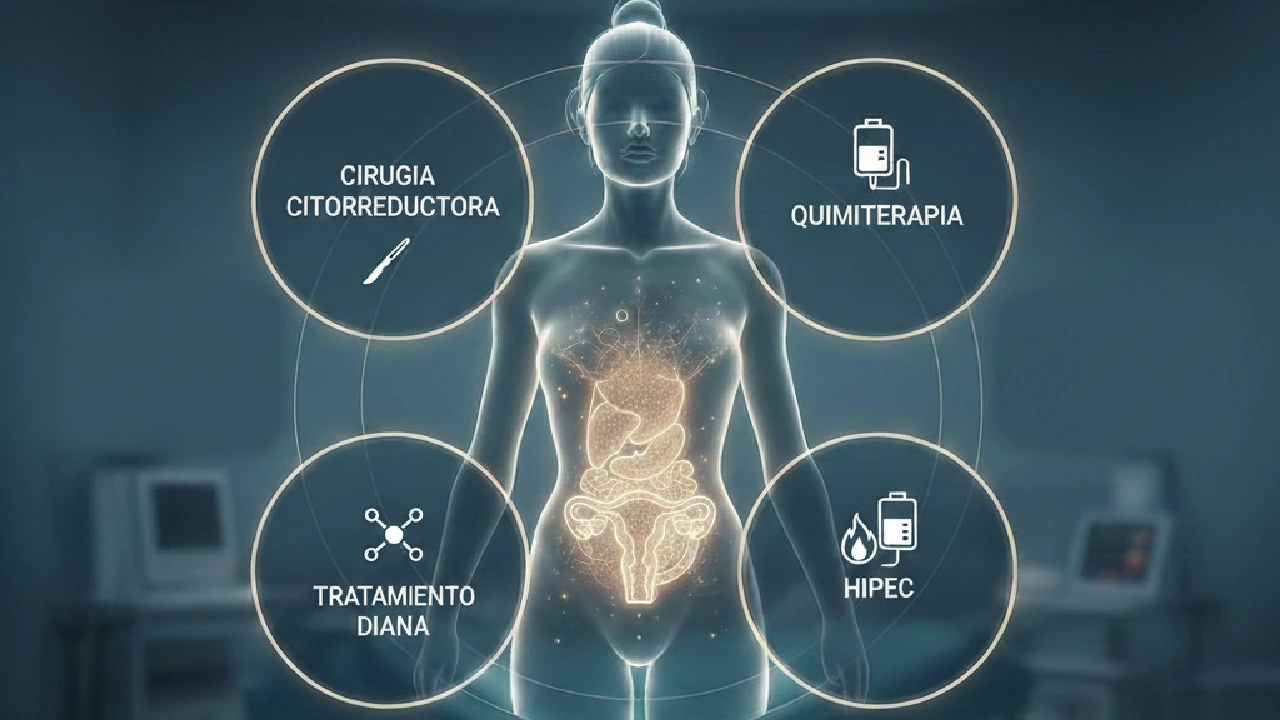
Treatment of ovarian cancer: a personalised approach
The treatment of ovarian cancer requires a multidisciplinary, personalised approach that combines surgery, chemotherapy and targeted therapies according to the stage, histological type and molecular characteristics of the tumour.
At Quenet Torrent Institute we follow current evidence-based protocols and include techniques such as HIPEC and targeted therapies when they are indicated.
Cytoreductive surgery: the main treatment
Cytoreductive surgery is the main treatment for ovarian cancer. The aim is to achieve complete cytoreduction (R0), removing all visible tumour. This significantly improves survival.
The operation typically includes removal of the ovaries, uterus, fallopian tubes and omentum (omentectomy) and, depending on the extent: peritoneal, intestinal or liver resections, splenectomy or diaphragmatic resections.
The surgeon's experience and the centre's case volume have a strong influence on the prognosis. Specialist centres like ours achieve optimal cytoreduction rates above 80-85%, compared with 40-50% in general hospitals.
HIPEC: hyperthermic intraperitoneal chemotherapy
HIPEC is used in selected cases of advanced ovarian cancer. At Quenet Torrent Institute we use it routinely.
After complete cytoreductive surgery, heated chemotherapy (41-43°C) is delivered directly into the abdominal cavity for 60-90 minutes. The heat enhances the cytotoxic effect and improves the penetration of the drug into residual micrometastases.
In selected patients with stage III-IV or recurrent platinum-sensitive ovarian cancer, HIPEC can increase median survival by 12-18 months.
Systemic chemotherapy
Chemotherapy is another basic part of ovarian cancer treatment and can be given at different times:
Adjuvant chemotherapy: After surgery in stages IC-IV. Usually 6 cycles of carboplatin and paclitaxel every 21 days.
Neoadjuvant chemotherapy: Before surgery in very extensive disease that is initially unresectable, to reduce tumour volume and make optimal cytoreduction easier ("interval debulking" strategy).
Maintenance chemotherapy: After completing initial treatment in patients who respond, to prolong the disease-free interval.
Palliative chemotherapy: In recurrence or inoperable metastatic disease, to control symptoms and prolong survival.
Targeted therapies: personalised medicine
PARP inhibitors: Olaparib, niraparib and rucaparib have changed maintenance treatment in patients with BRCA mutations or homologous recombination deficiency. They significantly improve progression-free survival.
Bevacizumab: An anti-angiogenic antibody that blocks VEGF. Used in combination with chemotherapy and as maintenance in advanced disease. It improves progression-free survival by 3-4 months.
Immunotherapy: PD-1/PD-L1 inhibitors are under investigation for subgroups with high microsatellite instability or a high mutational burden.
Treatment by stage
Early stage I-II: Complete surgery followed by adjuvant chemotherapy when there are high-risk factors. Survival >85%.
Advanced stage III-IV: Cytoreductive surgery + HIPEC + adjuvant chemotherapy + maintenance therapy (PARP inhibitors or bevacizumab). Survival 30-60% depending on cytoreduction.
Platinum-sensitive recurrence: Further cytoreductive surgery + HIPEC in selected cases + second-line chemotherapy + maintenance.
Platinum-resistant recurrence: Sequential palliative chemotherapy, targeted therapies, clinical trials.
Do you need a second opinion? Contact our ovarian cancer team so that we can review your case and explain your treatment options.